Pancreatic Cancer Treatment
Pancreatic cancer treatment isn't one standard plan. Most people searching for it want a single answer, but the real answer turns on one question: can the tumor be removed completely? Treatment usually combines surgery, chemotherapy, and radiation, and the mix depends on the tumor's stage and your overall health. This page explains each option, how the plan shifts from resectable to metastatic disease, and what to expect at every step.
Reviewed by Dr. P. Vijay Karan Reddy · Radiation Oncologist ·
Last updated October 2026
Pancreatic cancer treatment depends mainly on whether the tumor can be removed fully with surgery. Resectable tumors are usually treated with surgery, with chemotherapy before or after the operation depending on stage. Borderline and locally advanced tumors typically start with chemotherapy. Radiation can be added before surgery to shrink the tumor, or used when surgery isn't possible. Metastatic disease is treated with chemotherapy, aimed at controlling the cancer and easing symptoms.
Dr. Karan Explains Your Treatment Options
In this short video, Dr. Karan walks through how a treatment plan is built, what each option involves, and what to expect from your first consultation.
How Pancreatic Cancer Is Treated
Pancreatic cancer treatment almost always involves more than one approach. Surgery offers the only realistic chance of cure, but only when the tumor hasn't spread and can be removed with clear margins. For everyone else, chemotherapy usually comes first. Radiation can be added before surgery to shrink the tumor, after surgery in advanced cases, or used on its own when surgery isn't possible.
The National Cancer Institute lists FOLFIRINOX and gemcitabine with nab-paclitaxel as standard chemotherapy combinations. Targeted drugs and immunotherapy are only used when the tumor carries a specific genetic marker, so testing matters. Here's the thing: the diagnosis alone doesn't settle the plan. The scan, the tumor's genetics, and your fitness for treatment do.
The Best Treatment for Pancreatic Cancer Depends on Stage
Most plans combine two or more of these. Here's what each one does.
Surgery (Whipple or distal pancreatectomy)
A Whipple removes the head of the pancreas with part of the bowel and bile duct. Tumors in the body or tail need a distal pancreatectomy instead. It's the only route to cure, for resectable tumors.
With partner surgeonsChemo treatment for pancreatic cancer
Standard combinations include FOLFIRINOX and gemcitabine with nab-paclitaxel. Given before or after surgery depending on stage, to shrink a tumor or lower recurrence risk. It's also the main treatment for advanced disease.
With partner oncologistsRadiation therapy
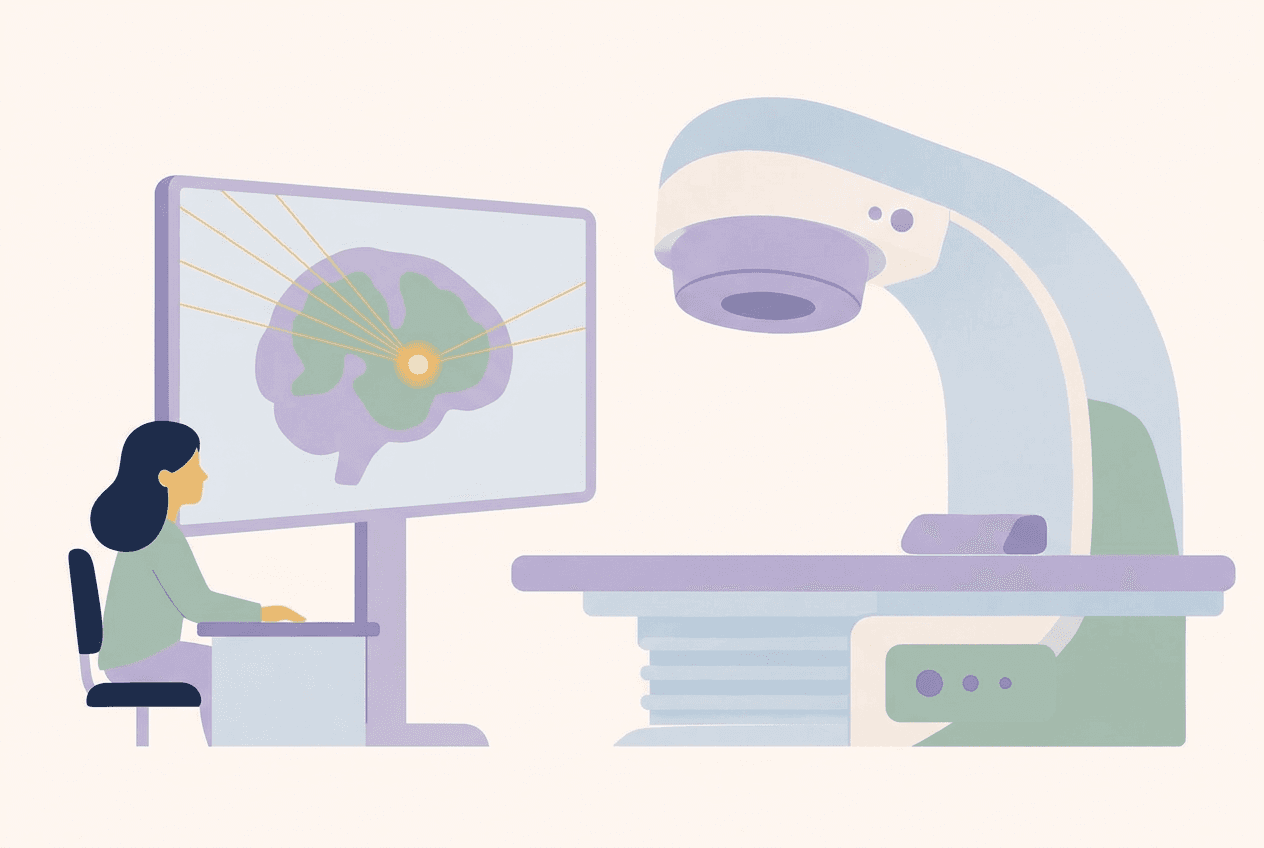
Image-guided radiation (IGRT) and stereotactic radiation (SBRT) are used for inoperable or advanced tumors, and SBRT is preferred. A regular course takes about 25 sessions. SBRT takes 5 to 7. It isn't only for pain control, because SBRT can be used with curative intent too.
Delivered by Dr. KaranTargeted therapy
Drugs that act on specific genetic changes in the tumor. They're only an option when testing finds a matching marker, which is why genetic profiling is part of the workup.
Discussed case by caseImmunotherapy
Helps the immune system recognize cancer cells. For pancreatic cancer it's used mainly in the small group of tumors with MSI-H or dMMR markers.
Discussed case by caseClinical trials and palliative care
Trials offer newer drugs for advanced disease. Palliative care manages pain, jaundice, and nutrition at any stage, and both can run alongside active treatment.
Discussed case by caseNot sure which treatment fits your tumor? Let's review your scans together.
Pancreatic Cancer Treatment by Stage
From resectable to advanced pancreatic cancer treatment, the plan turns on whether surgery is possible.
Resectable: surgery first (usually stage 1 or 2)
The tumor is confined to the pancreas and can be removed with clear margins. Surgery is the main step. Chemotherapy goes before or after the operation depending on stage, and when surgery comes first it's usually not needed afterward. Recovery takes weeks, and follow-up scans check whether the cancer returns.
Borderline resectable: chemo before surgery
The tumor touches major blood vessels, so surgery is possible but riskier. Chemotherapy comes first to shrink the tumor, and radiation can be added before surgery for the same reason. If it responds well, surgery may follow. If it doesn't, the plan changes.
Stage 3 pancreatic cancer treatment (locally advanced)
The tumor has grown around major vessels and can't be removed safely. Chemotherapy is the foundation. Radiation is added before surgery to shrink the tumor, after surgery in advanced cases, or as the main local treatment when surgery isn't possible. SBRT is preferred for these inoperable or advanced cases.
Stage 4 pancreatic cancer treatment (metastatic)
The cancer has spread to other organs, most often the liver. Chemotherapy is the main treatment, aimed at slowing growth and easing symptoms. The protocol changes with your fitness. Fit patients get a three drug combination, which is more effective. Frail patients get a one or two drug combination, which is still an effective first-line regimen but comparatively less so. Trials are worth asking about.
Pancreatic Cancer Treatment in India, Planned With Dr. Karan
Radiation planned personally
Dr. Karan designs and delivers the radiation part of your plan using IGRT and SBRT, with SBRT preferred for inoperable or advanced cases.
Decisions made at tumor board
Every case is reviewed at a weekly tumor board. Surgeons, oncologists, and radiation specialists agree on a plan that balances the best results with the fewest side effects.
Pancreatic experience
Dr. Karan has treated 20 to 30 patients with pancreatic cancer.
Plain, written options
You leave with a written summary of options, risks, and the reasoning behind each recommendation.
If surgery isn't the right route, Dr. Karan will say so and explain why. Surgery and chemotherapy are delivered by the surgical and medical oncologists at Apollo Hospital, Financial District, Hyderabad.
What to Expect, Step by Step
- 01
Consultation and report review
Bring your CT or MRI scans, pathology report, and blood test results. Dr. Karan goes through them with you and explains what each one shows.
- 02
Tumor board review
Your case is reviewed at the weekly tumor board. The team confirms one plan on the day of the meeting, and it's shared with you before treatment starts. The plan is evidence based, not tilted toward any one specialty, and it weighs your physical, mental, and social situation.
- 03
Simulation and planning
For radiation, a planning CT maps the tumor and nearby organs. A custom positioning setup keeps you still during every session. Your first session usually starts about 2 days after the planning scan.
- 04
Treatment sessions
A regular radiation course takes about 25 sessions. SBRT takes 5 to 7. Chemotherapy cycles follow your oncologist's schedule.
- 05
Follow-up
Scans and blood tests check whether the tumor is responding and watch for recurrence. The plan adjusts to what the results show.
Side Effects and How They're Managed
Will treatment affect how you eat? Often for a while, and most effects can be managed.
Worried about side effects? Dr. Karan will map them against your plan.
Rehabilitation and Supportive Care
Pancreatic cancer affects digestion, blood sugar, and comfort, so support matters as much as treatment.
Pancreatic Cancer Treatment Cost in India
There's no single price. These are the things that move it.
Surgery and chemotherapy
If surgery comes first, further chemotherapy is usually not needed, and the surgery costs around ₹5 lakh. Chemotherapy runs ₹60,000 to ₹70,000 per cycle, and a full course is 6 cycles.
Radiation technique and sessions
Radiation costs ₹2.5 to 4.5 lakh depending on the technique. The number of sessions matters too: about 25 for regular radiation, 5 to 7 for SBRT.
Hospital stay and supportive care
Length of stay, ICU needs, and ongoing diet or pain support all add to the total. Ask for an itemized estimate before you begin.
Many insurers cover cancer treatment, but pre-authorization is usually needed before surgery or chemotherapy starts. Ask the hospital's insurance desk to confirm coverage in writing.
Real Patients, Real Stories
Traveling from abroad for care? Ask Dr. Karan how the process works.
Questions to Ask Your Oncologist
Bring these to your first appointment, with Dr. Karan or anywhere else.
- Is my tumor resectable, borderline, or locally advanced?
- Would chemotherapy before surgery help my case?
- What is the goal of treatment at my stage?
- Which tests will check my tumor's genetic markers?
- Who coordinates surgery, chemotherapy, and radiation?
- What supportive care can we start now?
Questions Patients Ask Us
Surgery is the only route to cure, and only when the tumor can be removed completely. Many people are diagnosed after the cancer has spread, so treatment often aims at control.
It removes the head of the pancreas, part of the small intestine, the gallbladder, and the nearby bile duct. The remaining organs are reconnected so digestion can continue.
Yes. It's the backbone of treatment for most stages, given before or after surgery depending on stage, or as the main treatment for advanced disease.
Nausea, tiredness, and digestive upset are the most common. Most ease once treatment ends, and a dietitian can help you eat through them.
Only for a small group of tumors with specific markers, such as MSI-H or dMMR. Testing your tumor shows whether you're a candidate.
Often yes, especially for advanced disease. Eligibility depends on your tumor's genetics and the treatments you've already had.
About 14% of people with pancreatic cancer are alive five years after diagnosis, according to US National Cancer Institute SEER data from 2016 to 2022. Caught while still localized, that rises to about 44%, which is why stage-specific planning matters.
Yes. Stage 3 usually combines chemotherapy with radiation, given before surgery to shrink the tumor or when surgery isn't possible. Stage 4 relies mainly on chemotherapy and symptom care.
Most people spend days in hospital and need several weeks at home before regaining normal activity. Your surgical team will give a timeline based on your health.
Related Pages

Get a Clear Plan for Your Pancreatic Cancer Treatment
If you've been diagnosed with pancreatic cancer, a second opinion can confirm whether surgery is still possible and what the chemotherapy and radiation plan should look like. Send your scans and pathology report, and Dr. Karan will review them with you.

Written & reviewed by Dr. P. Vijay Karan Reddy ·
Radiation Oncologist · Last reviewed October 2026