Bone Marrow Transplant
A bone marrow transplant replaces diseased or damaged blood-forming cells with healthy ones. For many patients with leukemia, lymphoma, or certain blood disorders, it's the treatment that gives the best chance of a long-term cure. The transplant itself is led by a hematology and transplant team. Radiation oncology plays a specific part: delivering total body irradiation (TBI) to prepare the body for the new cells. This page explains what the transplant involves, what it costs, and what to expect.
Reviewed by Dr. P. Vijay Karan Reddy · Radiation Oncologist ·
Last updated October 2026
A bone marrow transplant replaces unhealthy blood-forming cells with healthy stem cells, from the patient or a donor. Patients usually receive high-dose chemotherapy, sometimes with radiation, before the infusion. The transplant is most often used for blood cancers and some inherited blood disorders. A hematology team leads it, and radiation oncologists deliver the total body irradiation component where used, mainly in allogeneic transplants.
Dr. Karan Explains Your Treatment Options
In this short video, Dr. Karan walks through how a treatment plan is built, what each option involves, and what to expect from your first consultation.
How a Bone Marrow Transplant Works
Bone marrow is the spongy tissue inside bones where blood cells are made. When disease takes it over or treatment damages it, the body can't make enough healthy blood. A bone marrow transplant replaces those cells with stem cells that can rebuild the system, taken from the patient (autologous) or from a donor (allogeneic or haploidentical), as the Mayo Clinic describes it.
Here's what most people don't expect: the infusion itself looks much like a blood transfusion. The hard work happens before it, in conditioning, and after it, in recovery. A hematology and transplant team leads the whole procedure. Dr. Karan's part is total body irradiation (TBI) within conditioning. It follows the protocol for an allogeneic transplant, and it can be myeloablative or reduced intensity.
Stages of the Bone Marrow Transplant Procedure
The transplant runs in stages. Here's what happens at each one, and who leads it.
Evaluation and donor search
The transplant team confirms the diagnosis, checks heart, lung, and kidney fitness, and searches family and registries for a donor if one is needed.
With partner transplant teamsStem cell collection
Stem cells are collected from the bloodstream or bone marrow, from the donor or from the patient before treatment, then stored until infusion.
With partner hematology teamsChemotherapy-only conditioning
High-dose chemotherapy clears diseased marrow and suppresses the immune system. Chosen when radiation isn't needed or suitable for the diagnosis.
With partner hematology teamsTBI-based conditioning
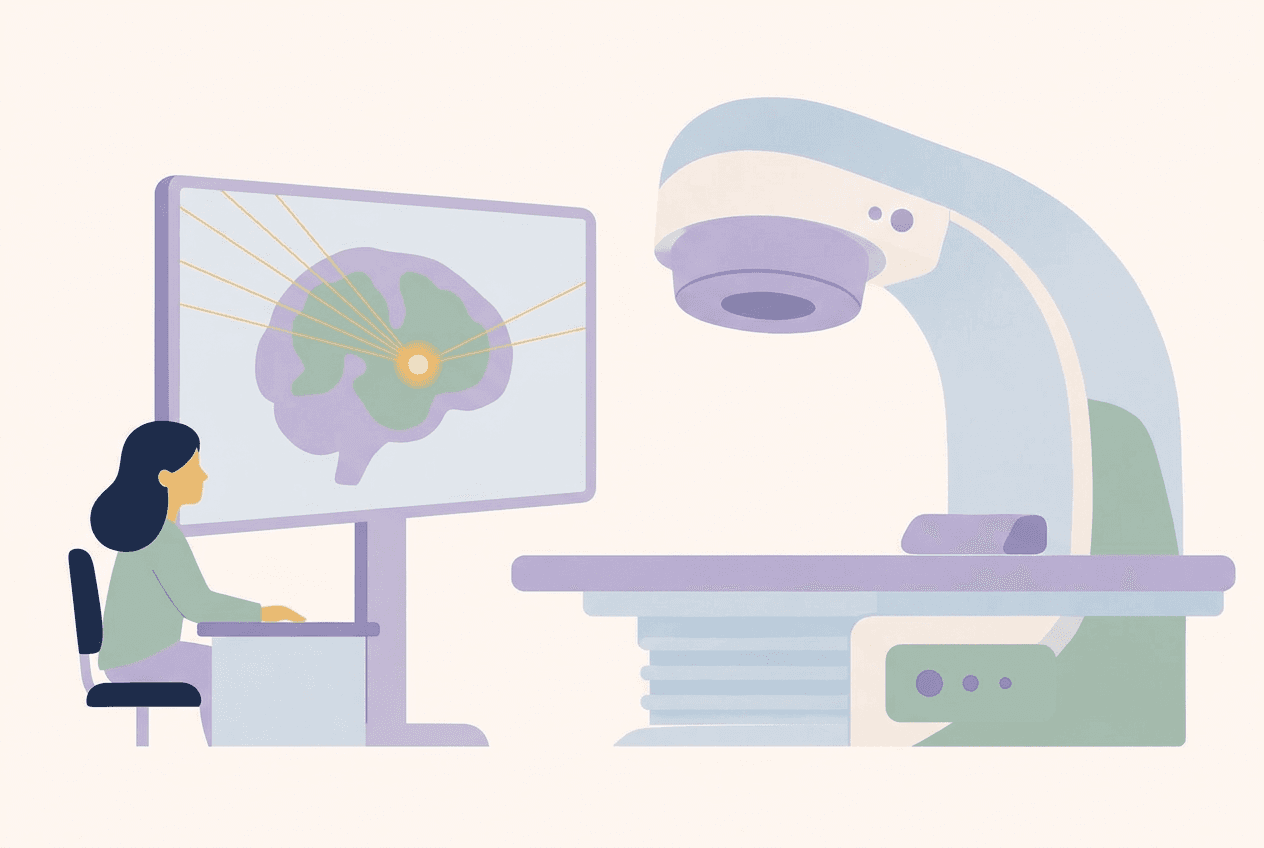
Radiation delivered across the whole body, usually with chemotherapy, to clear remaining disease and help donor cells take hold. It's used in allogeneic transplants, at myeloablative or reduced-intensity doses, and any technique can deliver it. Proton is preferable.
Delivered by Dr. KaranStem cell infusion
The new stem cells go in through a central line, much like a blood transfusion. It usually takes a few hours and isn't painful.
With partner transplant teamsEngraftment and recovery
Over the following weeks the new cells settle in the marrow and start making blood. Close monitoring guards against infection until counts recover.
With partner transplant teamsNot sure which transplant type fits your diagnosis? Send your reports to Dr. Karan for review.
Types of Bone Marrow Transplant
Choosing the type is the hematology team's decision, based on the diagnosis and the patient's health.
Autologous
The patient's own stem cells are used. There's no donor, so no risk of donor-related graft-versus-host disease, but the collected cells must be free of disease.
Allogeneic
Stem cells come from a donor, usually a sibling or an unrelated donor found through a registry. This can offer a stronger anti-disease effect, with a higher risk of graft-versus-host disease.
Haploidentical
A partly matched family donor, often a parent or child. Donors are usually easier to find, and transplant teams have refined this approach over the last two decades.
Syngeneic
Stem cells from an identical twin. This is rare, because it needs an identical twin donor.
Why Patients Choose Dr. Karan for Transplant Radiation
TBI experience
Dr. Karan has treated around 15 transplant patients with total body irradiation over the last 3 to 4 years.
Team-based care
Radiation planning is coordinated directly with the hematology transplant team at Apollo Hospital, Financial District, Hyderabad. The specialists there include a surgical oncologist, a medical oncologist, and a hemato-oncologist for bone marrow transplants.
Careful planning
Each TBI plan uses precise dose calculations and shielding for the lungs and other sensitive organs. TBI planning and delivery is only one part of the whole transplant plan, and the medical and hemato-oncologists handle your follow-up.
Honest guidance
You'll hear what TBI involves, what it costs, and what the realistic outcomes look like before any decision.
The transplant is a team decision. Dr. Karan's part is making the radiation safe and precise.
What to Expect, Step by Step
- 01
Consultation and report review
Bring your scans, blood reports, and biopsy results. Dr. Karan explains where TBI fits, while the hematology team leads the overall plan.
- 02
Transplant team review
The transplant team confirms the transplant type and conditioning plan, and whether TBI is part of it, before any radiation is planned.
- 03
Simulation and planning
Measurements and imaging map your body, and shielding is shaped for the lungs and other sensitive organs so the dose stays even and safe.
- 04
Treatment sessions
TBI is usually given over a few days just before the infusion, in short sessions where you stay still while the beam is on. TBI is given over 3 to 4 days, twice a day. The transplant admission itself usually lasts about a month.
- 05
Follow-up
The medical and hemato-oncologists run regular checks for years after transplant, watching blood counts, infection risk, and late effects on the eyes, lungs, and hormones.
Side Effects and How They're Managed
Every transplant carries real side effects. Here's what to expect and how the team manages each one.
Worried about side effects? Ask Dr. Karan what to expect from TBI and recovery.
Rehabilitation and Supportive Care
Recovery after transplant takes a team, not one specialist.
Bone Marrow Transplant Cost in India
There's no single bone marrow transplant price. It depends on the transplant type, the hospital stay, and the donor work.
Transplant type
Autologous transplants generally cost less than allogeneic ones, because donor search and testing add to the bill. Overall, a bone marrow transplant can cost anywhere from ₹15 to 20 lakh, depending on the protocol used and the hospitalisation needed. TBI is billed separately from the transplant.
Hospital stay
The length of stay, isolation room charges, ICU needs, and any complications all affect the total, often more than the transplant itself.
Donor and laboratory work
HLA matching, donor testing, stem cell collection, and lab processing are billed separately, and an unrelated donor search adds more.
Many insurers cover transplant under specific conditions. Check with your insurer before admission, and ask the hospital for a written, itemized estimate.
Real Patients, Real Stories
Coming from abroad for a bone marrow transplant in India? Send your reports ahead.
Questions to Ask Your Oncologist
Bring these to your appointment.
- Which transplant type do you recommend for my diagnosis?
- Is TBI part of my conditioning plan?
- Who leads the transplant, and who handles my radiation?
- What is the donor search timeline?
- What are the main risks in my case?
- How will you monitor me after transplant?
Questions Patients Ask Us
It replaces diseased blood-forming cells with healthy stem cells, from the patient or a donor. It's a treatment for blood cancers and some inherited blood disorders.
The infusion itself is short. TBI is given over 3 to 4 days, twice a day, and the transplant admission usually lasts about a month. The full pathway, including evaluation and recovery, runs for months.
Outcomes depend on the diagnosis, the transplant type, the donor match, and how fit you are going in. Your transplant team can give figures for your situation, usually quoted as survival at one year and beyond.
Nausea, fatigue, infection risk, and low blood counts are common early. Graft-versus-host disease can occur with donor transplants.
It depends on the transplant type, hospital stay, and donor work, and autologous transplants usually cost less than donor transplants. A transplant can range from ₹15 to 20 lakh depending on the protocol and hospitalisation, and TBI is billed separately. Ask for a written estimate before admission.
Recovery usually takes weeks to months, with follow-up for years.
It happens when donor immune cells attack the patient's body. It can be mild or serious, and it's managed with medication.
India's first bone marrow transplant was performed at Tata Memorial Centre, Mumbai, in 1983. Today it's offered at many specialist centers, for both blood cancers and inherited blood disorders.
Related Pages

Get a Clear Plan for Your Bone Marrow Transplant
Send your reports and diagnosis, and Dr. Karan will explain his TBI role, how it fits the transplant team's plan, and what to expect before any decision. International patients get the cost of the transplant as a package with no hidden costs, plus logistics support, including accommodation for the attenders.

Written & reviewed by Dr. P. Vijay Karan Reddy ·
Radiation Oncologist · Last reviewed October 2026