Colorectal Cancer Treatment
Colorectal cancer treatment combines surgery, chemotherapy, and sometimes radiation or targeted drugs. The right mix depends on the stage, the tumor's genetic profile, and whether the cancer started in the colon or the rectum. Radiation plays a much bigger role in rectal cancer than most people expect, and the reason is simpler than it sounds. This page walks through each option, how the plan changes by stage, and what to expect along the way.
Reviewed by Dr. P. Vijay Karan Reddy · Radiation Oncologist ·
Last updated October 2026
Colorectal cancer treatment combines surgery, chemotherapy, and sometimes radiation or targeted drugs. Many early-stage colon cancers are treated with surgery alone. Advanced disease usually needs chemotherapy, with targeted or immunotherapy drugs added based on tumor genetics. Radiation is used for rectal cancer, not colon cancer, because the tight pelvic space makes rectal cancer more likely to come back after surgery.
Dr. Karan Explains Your Treatment Options
In this short video, Dr. Karan walks through how a treatment plan is built, what each option involves, and what to expect from your first consultation.
How Colorectal Cancer Is Treated
Treatment depends mostly on where the cancer started and how far it has spread. Colon and rectal cancers are close relatives, but they're treated differently, and the gap matters most for radiation. Surgery to remove the cancer is the core of treatment wherever it's possible. Chemotherapy is added when there's a meaningful chance cancer cells have traveled beyond the tumor.
Why does location change the plan so much? The colon moves around inside the belly and sits next to the small bowel, which doesn't tolerate radiation well, so radiation isn't used for colon cancer. The rectum is fixed in a tight pelvis, where cancer is more likely to return. So radiation with chemotherapy before surgery is standard for stage 2 and 3 rectal cancer. Your team settles the final mix after reviewing your scans, pathology, and general health.
Treatment Options for Colorectal Cancer
Most plans combine two or three of these. Here's what each one does.
Surgery
Removes the part of the colon or rectum with the tumor, plus nearby lymph nodes. It's the main treatment for colon cancer at most stages, done open or by keyhole surgery.
With partner surgeonsChemotherapy
Drugs such as fluorouracil, often with oxaliplatin or irinotecan, reach cancer cells that may have spread. Given in stage 2 and 3 colon cancer, with radiation in stage 2 and 3 rectal cancer, and as the main treatment for advanced disease.
With partner oncologistsRadiation therapy
Precisely aimed beams that damage tumor cells. IMRT with IGRT is the basic technique for rectal cancer, given with chemotherapy before surgery in stage 2 and 3. Colon cancer doesn't get radiation.
Delivered by Dr. KaranTargeted therapy
Drugs that block specific molecules helping cancer grow. Tumor testing for RAS and BRAF decides whether drugs such as bevacizumab or cetuximab are suitable.
Discussed case by caseImmunotherapy
Helps the immune system recognize cancer cells. It works well for the small group of tumors that are MSI-H or mismatch repair deficient, but not for most others.
Discussed case by caseLiver-directed treatment
When cancer spreads to the liver, options include surgery, ablation, embolization, or liver-directed radiation. Whether it can be removed depends on how many spots there are and where.
Radiation by Dr. KaranNot sure which colorectal treatment fits your scans? Let's review them together.
Colorectal Cancer Treatment by Stage
Common approaches at each stage
Early stage colorectal cancer treatment (stage 1 and 2)
Stage 1 colon cancer often needs only surgery, while stage 2 colon cancer usually gets chemotherapy. Stage 1 rectal cancer is usually treated with surgery alone. Stage 2 rectal cancer gets radiation with chemotherapy before surgery.
Stage 3 colorectal cancer treatment
Cancer has reached nearby lymph nodes. For colon cancer, the standard plan is surgery followed by several months of chemotherapy, with no radiation. For rectal cancer, radiation with chemotherapy comes first, to shrink the tumor before surgery.
Stage 4 colorectal cancer treatment
Stage 4 means cancer has spread to distant organs, most often the liver or lungs. The aim is to control the disease and ease symptoms, with chemotherapy and targeted drugs at the core. Surgery on liver or lung spots is considered when it's possible. Dr. Karan's part is mainly liver-directed radiation when the cancer has spread to the liver. He only rarely uses radiation for symptom relief.
Recurrent colorectal cancer treatment
If colorectal cancer comes back, the plan depends on where it returns and which treatments were used before. Options can include surgery to remove a recurrence, chemotherapy, or radiation to control symptoms. A fresh review of scans and biopsy results comes first.
Why Choose Dr. Karan for Colorectal Cancer Care
Radiation oncology focus
Dr. Karan is a radiation oncologist, so his role centers on radiation planning, especially for rectal cancer.
Decisions made as a team
Every case goes to a weekly tumor board of surgical, medical, and hemato-oncologists, so you get one agreed recommendation.
Colorectal experience
Dr. Karan has 11 years in radiation oncology and has treated about 100 colorectal cancer patients with radiation.
Honest counsel
You'll get a plain explanation of options, likely outcomes, and costs before you decide anything.
Dr. Karan's view is that a clear stage diagnosis comes before any treatment choice. Surgery is delivered by partner surgeons at Apollo Hospital, Financial District, Hyderabad.
What to Expect, Step by Step
- 01
Consultation and report review
Bring your pathology report, scans, and blood tests. Dr. Karan reviews them and explains the stage and realistic options.
- 02
Tumor board review
Your case is reviewed at a tumor board held once a week. The plan is confirmed the same day and shared with you before treatment starts. It's evidence based and not tilted toward any one specialty. It weighs your physical, mental, and social situation, so the best results come with the fewest side effects.
- 03
Simulation and planning
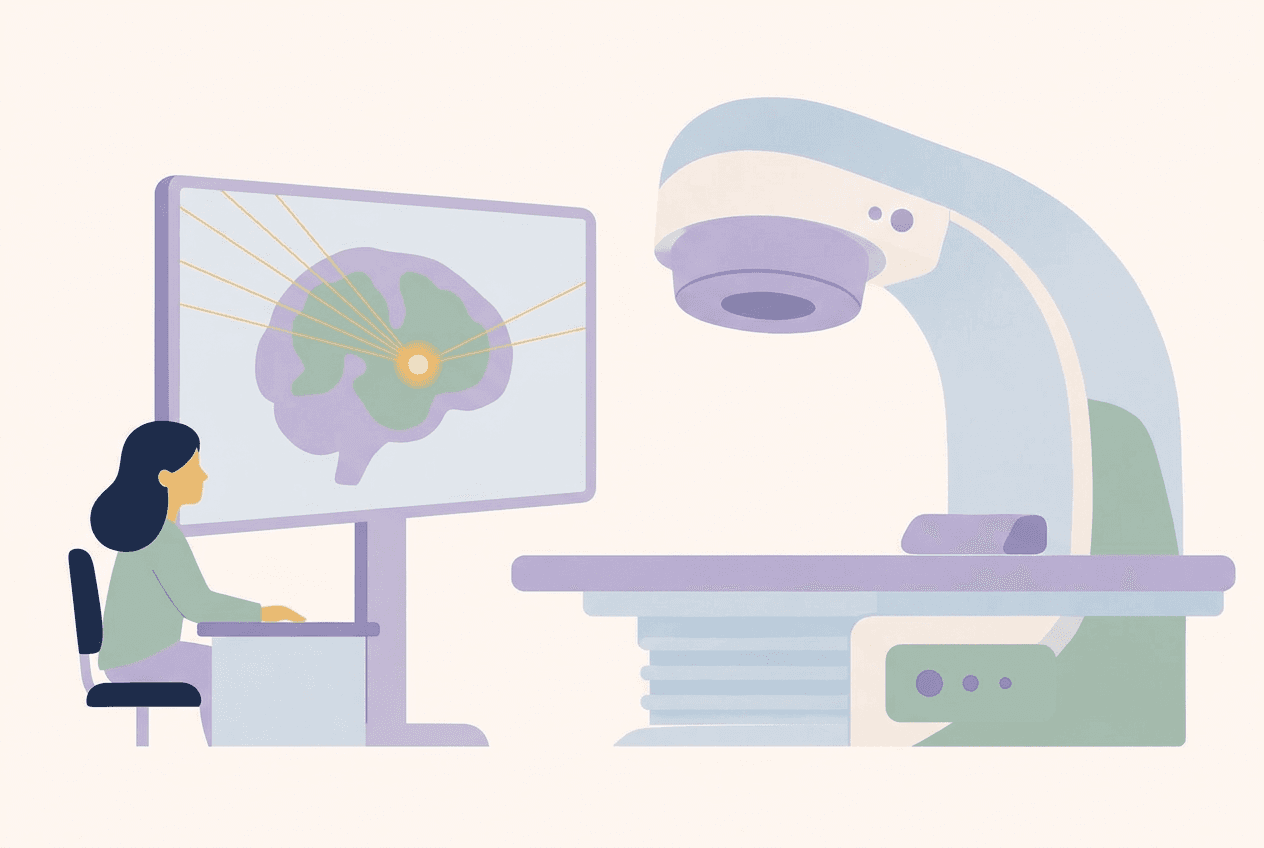
For rectal radiation, a planning scan maps the tumor so IMRT and IGRT beams can be aimed precisely and nearby organs are spared. Your first session usually starts about 2 days after the scan.
- 04
Treatment sessions
In stage 2 and 3 rectal cancer, radiation is given before surgery, either as 5 sessions or as 25 sessions. Most patients get the 25-session plan, on weekdays. Chemotherapy can run alongside it.
- 05
Follow-up
Scans and blood tests check how treatment is working. Follow-up continues for years, so any return is caught early.
Side Effects and How They're Managed
What to expect, and how it's handled
Worried about side effects? Dr. Karan will go through each one before you start.
Rehabilitation and Supportive Care
Recovery from bowel surgery and pelvic radiation takes more than treatment. All of these services are available through Dr. Karan's network.
Colorectal Cancer Treatment Cost in India
There's no single price. These are the things that move it.
Stage and treatment mix
Surgery alone costs far less than surgery with chemotherapy, targeted drugs, or chemoradiation. Each added step changes the total. Surgery typically costs ₹2.5 to 4 lakh. Radiation costs ₹2.5 to 4.5 lakh depending on technique. Chemotherapy runs ₹30,000 to ₹40,000 every 2 to 3 weeks, for 6 to 8 cycles.
Targeted and immunotherapy drugs
These are often the largest single line item, and they depend on genetic testing of the tumor.
Hospital and stay
Room type, operating time, and the number of nights in hospital all shift the final bill.
Many health insurance plans in India cover cancer treatment, but policies differ on chemotherapy drugs, radiation, and pre-authorization. Ask your insurer for written confirmation of what's covered before treatment starts.
Real Patients, Real Stories
Coming from abroad for colorectal cancer treatment in India? Send your reports ahead.
Questions to Ask Your Oncologist
Bring these to your appointment
- Is my cancer in the colon or rectum? Why does that matter?
- Has my tumor been tested for RAS, BRAF, and MSI status?
- Which treatments are standard for my stage, and which are optional?
- What is the goal of treatment: cure, control, or symptom relief?
- Which side effects should I report straight away?
- How will we know if the treatment is working?
Questions Patients Ask Us
Surgery, chemotherapy, radiation, targeted therapy, and immunotherapy are the main options. Most patients use a combination, chosen by stage and tumor genetics.
Surgery removes the part of the colon with the tumor and nearby lymph nodes. It's the main treatment for colon cancer, with chemotherapy added in stage 2 and 3.
Stage 4 colorectal cancer is usually treated to control it rather than cure it. Some patients with limited spread to the liver or lungs can be cured with surgery and chemotherapy.
Radiation uses precisely aimed beams (IMRT with IGRT), given with chemotherapy before surgery in stage 2 and 3. It's used for rectal cancer, not colon cancer, because the rectum sits in a tight pelvic space where cancer is more likely to come back.
It works well for a small group of tumors with high microsatellite instability and doesn't help most others. Testing decides who qualifies.
Targeted therapy blocks specific proteins that help cancer grow, such as those targeted by bevacizumab or cetuximab. Genetic tests on the tumor show which drugs are suitable.
Fluorouracil-based regimens, often with oxaliplatin (FOLFOX) or irinotecan, are standard combinations. The exact choice depends on stage and your health.
About 65% of people with colorectal cancer are alive five years after diagnosis, according to US National Cancer Institute SEER data from 2016 to 2022. Found while still localized, that rises to about 91%, which is why screening and early checks matter.
Related Pages

Get a Clear Plan for Your Colorectal Cancer Treatment
Whether you're just starting out or want a second opinion on a plan you already have, a focused consultation gives you clear answers. Bring your reports and scans. You'll leave knowing your options, the next steps, and what to ask your team.

Written & reviewed by Dr. P. Vijay Karan Reddy ·
Radiation Oncologist · Last reviewed October 2026